Premature babies · October 12, 2026
A probiotic given to very premature babies took hold in the gut within a week. The title says it is linked to better brain white matter. The brain scans of the two groups did not differ
In a Dutch neonatal unit, babies born at 24 to 30 weeks got a daily Bifidobacterium, prebiotic fibres and glutamine, or a placebo. The bacterium settled in almost every baby who got it, and in four in ten who didn't. The link to the brain comes from a later comparison of babies with and without a scan finding, whichever group they were in.
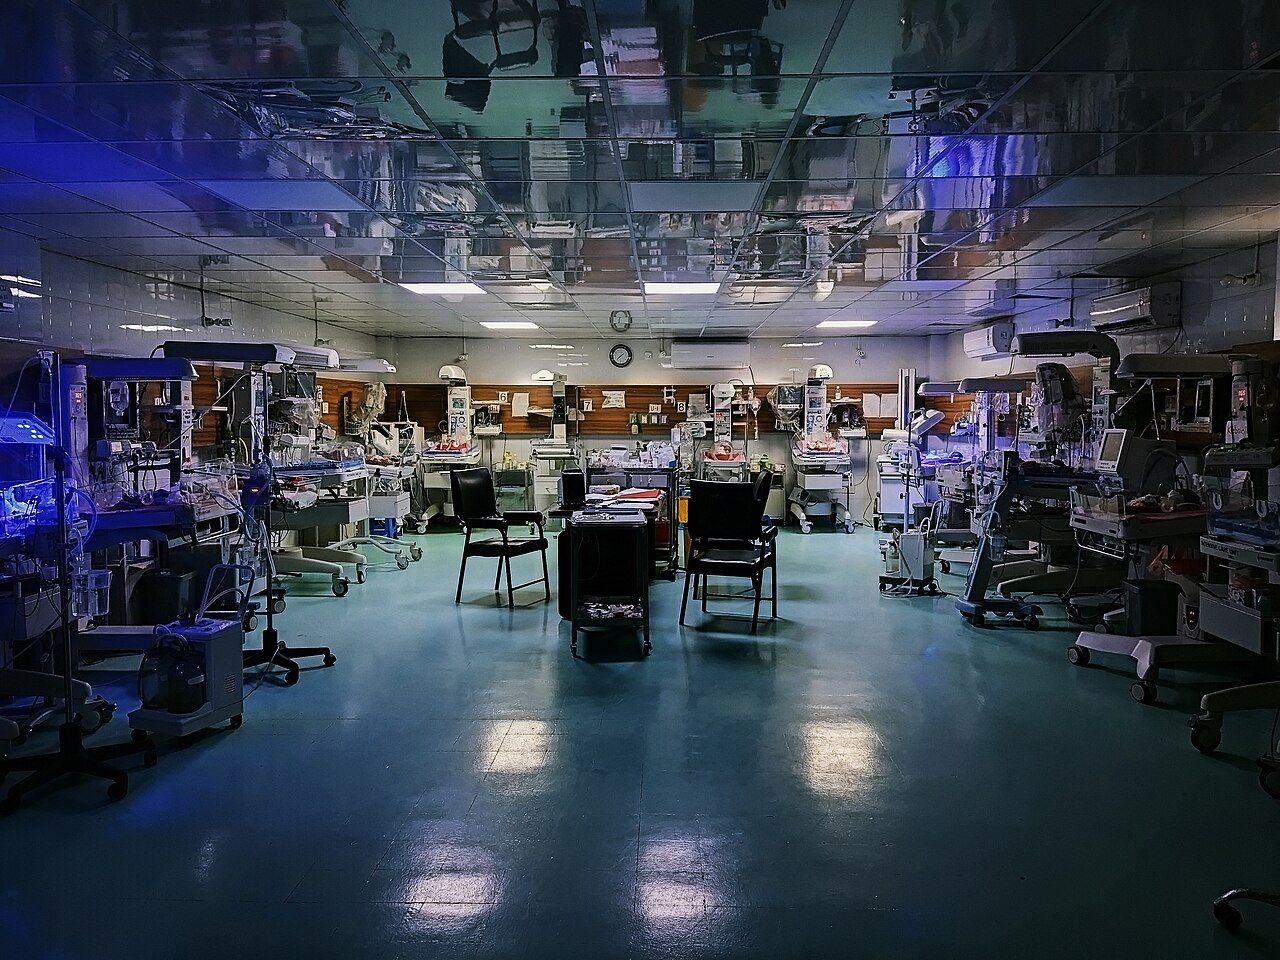
A baby born at full term and breastfed usually ends up with a gut full of Bifidobacterium within weeks. A baby born three months early does not. The first settlers tend to be Staphylococcus, then Enterococcus and the Enterobacteriaceae family, and the bifidobacteria arrive late. Those same early weeks are when the brain's wiring is being laid down and insulated, work that would otherwise have happened in the womb. So neonatal researchers have a reasonable question: if you get the friendlier bacteria in sooner, does the brain do better? A Dutch team from Wageningen University, the Wilhelmina Children's Hospital in Utrecht and Danone Research & Innovation published their attempt at an answer in the journal Gut Microbes on 7 October 2026.
The trial behind it was double-blind and ran in the neonatal intensive care unit in Utrecht, with babies followed into seven regional hospitals when they were transferred. Parents of 338 eligible babies were approached, and between October 2018 and May 2022, 99 babies born at 24 to 30 weeks were randomised. From two to three days after birth until 36 weeks, or going home, half were given a daily dose of Bifidobacterium breve M-16V by feeding tube or syringe, along with a prebiotic mix of two oligosaccharides and the amino acid L-glutamine added to their milk. The other half got lookalike powders made of maltodextrin and milk proteins. Stool was collected from the first days onward, and each baby had a brain MRI at around the date they should have been born.
On the gut side, the result is clear. One week in, the given strain could be found in 97% of the babies who received it and 9% of those who did not. Bifidobacterium as a whole was more abundant in the supplemented babies through week 6, Staphylococcus was lower at week 1 and Enterococcus lower at week 3. The bacteria in the supplemented babies also carried more of the genetic equipment for making amino acids and for fermenting pyruvate into acetate and lactate. After week 6 the two groups could no longer be told apart on any of this. The authors call the colonisation 'robust but transient'. Weight gain was the same in both groups.
Now the brain, which is what the title is about. The paper's own sentence is: 'No significant differences in the assessed brain injury markers were observed between the intervention and control groups.' The babies who got the supplement did not have better scans than the babies who got placebo. What the team did next was a post hoc analysis, meaning one decided on after the data were in. They set the randomised groups aside and compared babies by what their scan showed. The 20 babies with delayed myelination of white matter had a different mix of gut bacteria at week 3 from the 45 without it, with less Bifidobacterium breve and less capacity for pyruvate fermentation. The 11 babies with a thinned corpus callosum differed at week 1 from the 52 without. The fermentation pathways that were lower in the babies with delayed myelination were the same ones the supplement had raised.
That is two separate findings placed next to each other: the supplement changed the gut bacteria, and the gut bacteria looked different in babies with two particular scan findings. It is not a finding that the supplement changed the scans, because when that was tested directly it showed nothing. The second finding is also an observation, not an experiment. A baby who is sicker in the first weeks may have both a disturbed gut and slower brain development for reasons that have nothing to do with one causing the other. And the team looked at a long list of scan measures. Two were tied to the bacteria. The rest, including the direct measurements of white-matter structure taken from diffusion imaging, were not.
There are practical complications as well. By week 3 the probiotic strain was showing up in 44% of the placebo babies. Bacteria travel around a neonatal unit on hands and equipment, and this is common in probiotic trials. It blurs the comparison, and the authors say it may have hidden some of the effect. That is possible, though it cannot be shown from this trial. Of the 99 babies randomised, 84 had usable stool data and 76 of those had a usable scan. The trial's size was set for its main question, not for this analysis. And because three things were given together, nothing here says which of the bacterium, the fibres or the glutamine did what.
Who paid matters. The work was funded by a Dutch public grant with co-financing from Danone Research & Innovation, and five of the authors are Danone employees. The paper states that they took no part in the microbiome or MRI analysis. The abstract ends by saying the study 'demonstrated that early microbial modulation could influence brain development'. On the evidence in the paper, 'could' is doing a lot of work in that sentence.
Our reading: this is good evidence that a daily Bifidobacterium breve with prebiotics settles into the gut of a very premature baby within a week and shifts the early bacterial mix for about six weeks. It is a lead, not evidence, that this does anything for the brain. The same trial compared the scans and found no difference between the groups. The honest next step is a trial sized to answer the brain question, with the children's development followed for years. For parents of a premature baby, the practical point is short. Whether a baby in a neonatal unit gets a probiotic, and which one, is a decision for the neonatal team. Products sold to the public are not made or tested for babies this small and should never be given without the team's say.
Secondary analysis of a double-blind randomised trial in Utrecht, the Netherlands: babies born at 24 to 30 weeks given daily Bifidobacterium breve M-16V, prebiotic oligosaccharides and L-glutamine, or placebo, from days 2 to 3 of life until 36 weeks
No difference
Brain injury and maturation markers on MRI at term-equivalent age, supplement group against placebo group (chi-squared tests, all p above 0.05)
97% vs 9%
Babies in whom the given strain was detected at week 1 (above 0.5% of gut bacteria): supplement group against placebo group. Paper's figures 97.3% and 9.1%
44%
Placebo babies carrying the probiotic strain by week 3 (39% at week 6), picked up on the unit. In the supplement group: 100% at week 3, 94% at week 6
20 vs 45
Babies with and without delayed white-matter myelination on the scan. Their week 3 gut bacteria differed (ANOSIM R = 0.25, p = 0.001), in a post hoc comparison that ignores which group they were in
99 → 84 → 76
Babies randomised, babies with usable stool sequencing (473 samples), and babies who also had a usable brain scan
6 weeks
How long the groups' gut bacteria stayed measurably different. No differences in bacterial make-up or function were found at later sampling points
Figures are from the paper in Gut Microbes (2026;18(1):2743949, published online 7 October 2026), read on the publisher's site: abstract, introduction, methods, results text, discussion, funding and disclosure statements. Table 1 (the babies' characteristics), the figures and the two supplementary files were not read, so we give no group sizes, birth weights or sex split, and we do not know how many of the 84 or 76 babies were in each group. The paper presents the microbiome as the main outcome of this analysis and describes the brain associations as post hoc. It does not report the parent trial's primary result beyond the sentence on brain injury markers quoted in the story. Doses: the bacterium at 3 billion colony-forming units a day (1.5 billion to start for babies under 1,000 g), the oligosaccharide mix (short-chain galacto-oligosaccharides and long-chain fructo-oligosaccharides, 9:1) rising to 0.6 g per kg a day and L-glutamine to 0.3 g per kg a day at full feeds. Other results: gut communities differed between groups at week 1 (ANOSIM R = 0.4, p < 0.001), week 3 (R = 0.10, p < 0.001) and week 6 (R = 0.06, p = 0.003), so the gap shrank over time; Bifidobacterium higher at weeks 1, 3 and 6 (p = 7.9 × 10⁻¹⁰, 0.006, 0.042); Staphylococcus lower at week 1 (p = 0.017); Enterococcus lower at week 3 (p = 0.008). Corpus callosum thinning: 11 babies with and 52 without, week 1 communities differed (R = 0.20, p = 0.017). The two pyruvate fermentation pathways differed between babies with and without delayed myelination by log2 changes of 1.34 (p = 4.93 × 10⁻⁴) and 1.47 (p = 0.003). A higher ratio of Enterobacter roggenkampii to B. breve at week 3 pointed to delayed myelination (AUC 0.78) and of Staphylococcus haemolyticus to B. breve at week 1 to corpus callosum thinning (AUC 0.75). Sex, type of milk (mother's milk or preterm formula), delivery mode and gestational age band were not linked to differences in gut bacteria; antibiotics were, at week 3 only, with 9 of 73 sampled babies receiving them. The pathway results describe what the bacteria's genes could do, read from DNA; acetate and lactate themselves were not measured, which the authors list as work for future studies. The numbers with and without each scan finding add up to 65 and 63, not 76, because not every baby had a stool sample at each time point; that is our inference. The remark that sicker babies may have both a disturbed gut and slower brain development is ours, not the paper's. Two slips in the text as published: one gestational age band is printed as '24–16' weeks, and the discussion says 'HMOs were used' where the methods describe the galacto- and fructo-oligosaccharide mix, which is not human milk oligosaccharides. Limitations the authors state: secondary analysis with the sample size set for another endpoint, babies lost between enrolment and analysis, a single centre, cross-colonisation of control babies, one strain tested. Funding: the Athena Grant of the Utrecht Center for Food and Health (Dutch Ministry of Economic Affairs, Utrecht Province, municipality of Utrecht) with co-financing from Danone Research & Innovation. Trial registration ISRCTN96620855.
- 'Term-equivalent age' is the date a premature baby was due. A baby born at 26 weeks reaches it about 14 weeks after birth, and that is when the brain scans in this study were done, on a 3-tesla MRI scanner.
- Myelin is the fatty coating that insulates nerve fibres so signals travel fast. Much of it is laid down in the last months of pregnancy and the first years of life, which is why a delay shows up on a scan of a baby born early.
- The corpus callosum is the thick band of nerve fibres joining the left and right halves of the brain. Radiologists scoring a premature baby's scan check whether it looks thinner than expected.
- The paper cites an estimate that about 11% of births worldwide are preterm, and that two-thirds of them happen with no evident risk factor.
- The team could tell the given bacterium from other Bifidobacterium breve because they sequenced all the DNA in each stool sample and matched it to the strain's published genome. That is how they knew it had spread to babies on placebo.
- Synbiotic supplementation leads to gut microbiome communities with functional capacity linked to better brain white matter development in preterm infantsGut Microbes, 7 October 2026 · The study
- Full text on the journal's siteTaylor & Francis · Read: main text, funding and disclosures. Table 1, figures and supplements not read
- PubMed record (PMID 42841652)US National Library of Medicine · Abstract and authors
- Trial registration ISRCTN96620855ISRCTN registry · Registration cited in the paper; not read for this item
- Night at NICUWikimedia Commons · Image, CC0, Realistroot
General information, not medical advice. This study does not show that a probiotic improves brain development in premature babies. Never give a probiotic or any supplement to a premature or unwell baby yourself; what a baby in neonatal care receives is decided by the neonatal team. If you have questions about your baby's feeding or development, ask the doctors and nurses looking after them.
Analysis by NutroPractic from the sources listed. Written for general readers; it does not replace advice from your own doctor.
From our articles
Our guides on this subject
Plain-language guides on nutrition and wellness, backed by research.

Everyday eating
The fibre gap: why most adults fall short, and an easy 30-gram day
Most adults in the US, Canada and Europe eat far less fibre than recommended, even though higher intakes are linked to lower rates of heart disease, type 2 diabetes and bowel cancer. How much you need, where it hides, and a sample day that gets you to 30 grams.
3 Oct 2026

Global data
Diabetes, obesity, child malnutrition and hunger, 1980 to 2050: what the numbers show
How diabetes, obesity, child malnutrition and hunger have changed since 1980, with sourced figures and a basic projection to 2050. Click a condition to explore the chart and its facts.
5 Oct 2026

Indian kitchen
Rice, roti and blood sugar: building a balanced Indian plate with the ICMR-NIN 2024 guidelines
About one in nine Indian adults has diabetes and many more have prediabetes. You don't have to give up rice or roti. How the ICMR-NIN Dietary Guidelines for Indians (2024) suggest building a plate, plus simple habits that help keep blood sugar steady.
3 Oct 2026
Newsfeed for your website
Want this feed on your website?
Add it to any site with one copy-and-paste snippet. No sign-up, and it updates itself every hour.
Start with a virtual consultation
Tell Dr. Triveni what you want to change. You will leave with a clear next step, whether you are in Toronto, London, New York or Chennai.